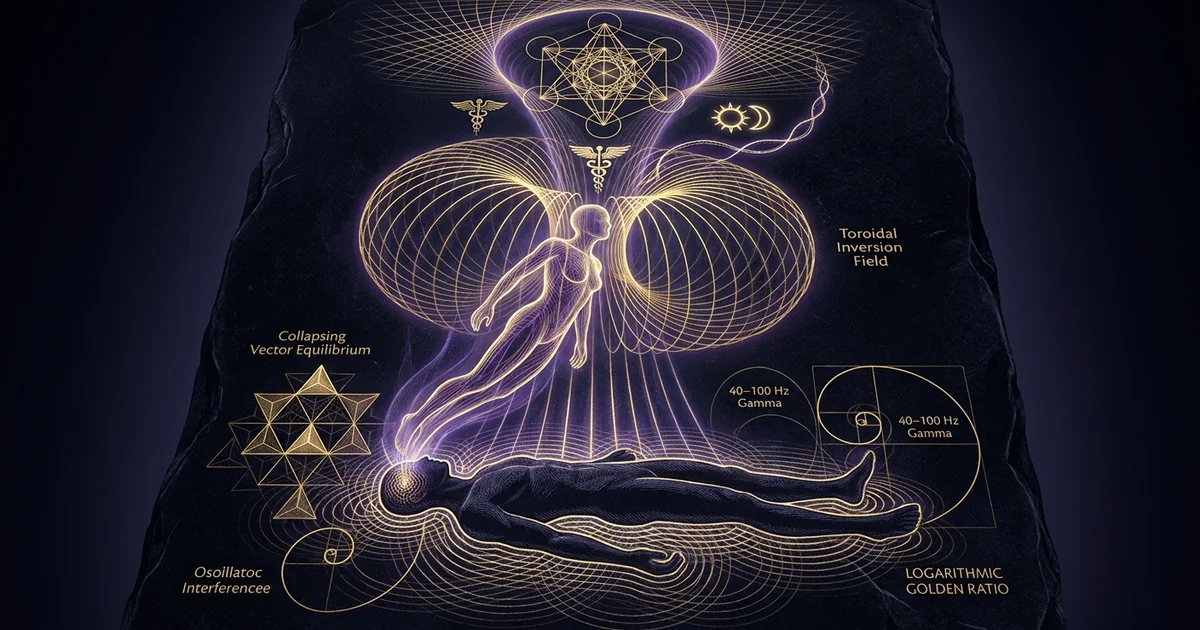
The Vibrational Stage: Somatic Tremors Before Astral Exit
1. Protocol Overview & Neurophysiological Thesis of Somatic Tremors
1.1 The Threshold Phenomenology: Mapping the Pre-Separation Tremor
The onset of spontaneous or protocol-driven extra-somatic projection is routinely heralded by an acute, localized or whole-body tremor known in transpersonal literature as the vibrational state. Far from manifesting as an amorphous somatic drift, this subjective phenomenon presents as a distinct, rapid-frequency oscillation—perceived internally as an intense energetic humming, galvanic surging, or fine-grained mechanical trembling through the skeletal and muscular frameworks. Subjects crossing the threshold of astral separation consistently describe this tremor not as a muscular fasciculation observable by external monitors, but as an endogenous, high-velocity resonance that bypasses gross kinetic activity entirely.
This transitional state marks the inflection point between standard waking consciousness and somatosensory decoupling. The subject remains fully aware of their immediate environment yet perceives their somatic boundaries disintegrating into dynamic energetic flux. During this phase of the vibrational stage out of body experience somatic vibrations, ambient acoustic phenomena frequently transform: internal auditory perceptions shift from hypnagogic murmurings to an overt, high-pitched carrier whine, a rushing wind, or rhythmic, deep-frequency electrical pulses.
Crucially, the preservation of reflective self-awareness throughout these somatic tremors distinguishes the experience from generic sleep-wake transitions. The reflective ego observes the physiological substrate entering what appears to be an anomalous motor-sensory arrest. Stabilizing this threshold requires resisting the somatic urge to terminate the oscillation via gross motor recruitment, allowing the neuromuscular framework to yield to deep neuro-electrophysiological re-patterning.
1.2 Temporoparietal Junction (TPJ) Attenuation and Disrupted Somatosensory Binding
The core neurobiological mechanism governing this vibrational threshold resides within the multimodal integration centers of the cerebral cortex, specifically the right temporoparietal junction (rTPJ). Under baseline conditions, the rTPJ continuously binds vestibular inputs, somatosensory tactile data, visual references, and proprioceptive afferents into a coherent egocentric frame of reference. This spatial localization anchors the phenomenological self directly inside the physical anatomy, providing an uninterrupted sense of embodiment.
“Focal electrical stimulation of the right temporoparietal junction in a patient undergoing evaluation for epilepsy repeatedly induced out-of-body experiences, vestibular illusions, and illusory transformations of the patient’s own body… These findings indicate that out-of-body experiences reflect a failure of integration of personal somatosensory, vestibular, and visual processing, culminating in the phenomenal disruption of the self residing within the physical frame.” — Blanke, O., Landis, T., Spinelli, L., & Seeck, M. (2004). Out-of-body experience and autoscopy of neurological origin. Brain, 127(2), 243–258; with supplementary corroboration in De Ridder, D. et al. (2007). Visualizing out-of-body experience in the brain. New England Journal of Medicine, 357(18), 1829–1833.
When sensory de-afferentation occurs alongside retained cortical lucidity, the computational integrity of the rTPJ breaks down. Somatosensory afference drops precipitously, but central motor intentions or autonomic monitoring routines continue firing. Deprived of the continuous mechanical and proprioceptive feedback loops that establish somatic boundary definitions, the rTPJ generates an error signal characterized phenomenologically by high-frequency spatial jitter. The sense of spatial stability shatters, and the perceptual machinery of the brain registers this computational decoupling as a rapid, violent oscillation running along the somatic axis.
This functional disconnect does not represent neural pathology; rather, it reflects the uncoupling of spatial reference frames. The internal body schema separates from the physical sensory apparatus, generating the sensation of an oscillating subtle-body undergoing release from dense tissue constraints. Advanced neuroimaging indicates that down-regulation of the right angular gyrus and supramarginal gyrus directly precedes the re-anchoring of the self in an extracorporeal spatial position, confirming that the subjective vibrational surge directly mirrors the unbinding of multisensory integration matrices.
1.3 The Vestibular-Motor Dissociation Hypothesis
A secondary physiological driver of somatic tremors emerges from vestibular-motor dissociation. In classical neuromuscular activation, the vestibular system calculates gravitational orientation and sends corrective signals down the vestibulospinal tracts to modulate postural tone. When conscious relaxation deepens toward stage R or hypnagogic boundaries, this feedback circuit faces acute desynchronization. The otolithic organs continue signaling gravitational orientation, while the central motor system imposes pre-synaptic motor inhibition across the spinal cord.
The mismatch between an active inner-ear sensory channel and an immobilized peripheral effector network generates an intense interoceptive sensory illusion. The somatic sensorium interprets the absence of expected mechanical feedback as rapid micro-accelerations in multiple directions at once, creating a feeling of floating, sinking, or rapid planar vibration. Because the brain cannot reconcile active cognitive intention with zero motor feedback from somatic effectors, the perceptual construct of the body experiences profound oscillatory instability.
Navigating this threshold requires absolute psychological equilibrium. If the practitioner interprets this vestibular-motor dissociation through the lens of threat, the amygdaloid complex triggers an abrupt burst of high-frequency Beta activity. This panic cascade prompts an immediate adrenergic release that violently breaks the delicate motor atonia, instantly terminating the vibrational stage. Conversely, when sustained within a stable, parasympathetically anchored Theta framework (4–7 Hz), the dissociation stabilizes, allowing the conscious observer to cross the boundary into veridical extra-somatic perception.
2. Biophysical Mechanisms: Psychoacoustics, FFR, and Neurotransmitter Dynamics
2.1 Frequency Following Response (FFR) and Binaural Phase Cancellation
The induction and stabilization of pre-separation somatic tremors can be systematically catalyzed through acoustic interventions designed to evoke the Frequency Following Response (FFR). By exploiting the brain’s tonotopic and phase-locking neurophysiology, precise acoustic inputs steer the global cortical architecture toward specific oscillatory boundaries required for somatosensory uncoupling. This process relies on auditory processing within the superior olivary complex, located in the lower brainstem.
When two distinct acoustic carrier waves with a minute frequency differential—for example, a 196 Hz tone to the left ear and a 201.5 Hz tone to the right ear—are delivered dichotically through stereo isolation, the primary auditory cortex cannot process them as separate spatial sources. Instead, neurons within the medial superior olive engage in phase-sensitive summation, outputting a dynamic, amplitude-modulated composite waveform at the difference frequency of 5.5 Hz. This endogenous phantom beat provides a continuous phase reference for widespread thalamocortical circuits.
Through prolonged acoustic exposure, large populations of cortical neurons align their firing rates with this binaural beat, precipitating hemispheric-synchronization across bilateral fronto-parietal networks. As the FFR shifts dominant cortical rhythms into the lower Theta continuum (4–6 Hz), the waking sensorimotor networks lose their coherence. Proprioceptive afference is systematically attenuated, bringing the somatic envelope directly to the threshold of mechanical decoupling. More expansive parameters and waveform formulations for this acoustic framework are detailed in the foundational study of binaural beats brainwave entrainment.
2.2 Ascending Reticular Activating System (ARAS) Gating and Glycine-Mediated Motor Atonia
Somatic tremors require a delicate neurochemical landscape: the Ascending Reticular Activating System (ARAS) must selectively lower somatic vigilance while maintaining clear thalamocortical cognitive processing. In standard sleep architectures, the transition to deep unconsciousness involves a global suppression of the ARAS, cutting sensory processing via non-specific thalamic nuclei and reducing baseline cholinergic activity across the forebrain.
In the controlled vibrational threshold, this balance is disrupted. Pontine structures—specifically the sublaterodorsal nucleus (SLD)—activate early while the prefrontal cortex remains fully conscious. The SLD projects ventrally to premotor interneurons within the ventral medial medulla, which subsequently send descending projections down the reticulospinal tracts to the anterior horn cells of the spinal cord. Here, the neurotransmitters glycine and gamma-aminobutyric acid (GABA) are co-released directly onto somatic motor neurons.
This floods the motor system with post-synaptic inhibitory potentials, causing rapid hyperpolarization that blocks physical movement—the neurobiological definition of sleep-paralysis. Concurrently, serotonergic output from the dorsal raphe and noradrenergic projections from the locus coeruleus collapse toward zero, matching the neurochemical profile of rapid eye movement states while conscious executive control remains active. The subjective electromagnetic buzzing body is the visceral perception of the physical frame dropping into motor atonia while conscious attention remains hyper-vigilant.
2.3 High-Gamma Oscillatory Bursts (40–100 Hz) Interspersed on Slow Theta Baselines
While slow-frequency Theta rhythms anchor the practitioner’s gross bioelectric baseline, the subjective sensation of an internal high-voltage hum reflects a very different electrophysiological mechanism: transient bursts of high-Gamma oscillatory activity (40–100 Hz) operating across decentralized cortical zones.
During standard waking consciousness, localized Gamma oscillations bind sensory features across different cortices into unified perceptual moments. When the physical body enters complete atonia and somatosensory inputs cease, these cortical regions enter an uncoupled state. Motor strips, somatosensory pathways, and association areas begin firing coherent Gamma bursts unconstrained by physical sensory input. Because the spinal motor gates remain closed via glycinergic inhibition, this electrical activity cannot dissipate through muscle movement.
       Gamma Bursts (40-80 Hz) -> [||||||||||||||||||||||||||||||||||]
                              \      /      \      /      \      /
  Theta Carrier Ground (5.5 Hz) -> \    /        \    /        \    /
                                    \__/          \__/          \__/
As illustrated above, these intense micro-gamma bursts fire across the sensorimotor cortex, riding on the slow, high-amplitude Theta carrier wave. The conscious observer experiences this neural synchronization as a fine-grained, intensely visceral somatic buzz. This high-frequency dynamic confirms that the vibrational stage is not a state of neural torpor, but a highly active, focused neurological transition phase where internal bioelectric currents reach peak coherence.
3. The Gateway Cadence: Monroe’s Vibrational Mechanics and Historical Precedents
3.1 Robert Monroe’s Discovery: The Non-Physical Energy Accumulation Model
The modern systematic study of somatic tremors began with radio executive and consciousness researcher Robert A. Monroe. In the late 1950s, Monroe began experiencing spontaneous somatic vibrations accompanied by total motor paralysis and auditory roaring, phenomena he initially feared were symptoms of impending cerebrovascular failure. Finding no neurological pathology upon extensive clinical evaluation, Monroe turned his empirical attention to cataloging the mechanics of the threshold.
Monroe mapped the progression of the vibrational stage in his foundational text Journeys Out of the Body (1971). He identified the tremors as an accumulation of non-physical energetic potential within the somatic structure. According to his records, the experience follows an invariant cadence: an initial localized tingling or thermal wave quickly accelerates into a pervasive, high-frequency vibration running cranio-caudally between the crown of the head and the soles of the feet. Monroe observed that attempts to resist this oscillation through physical muscular contraction induced immediate kinetic shock and aborted the projection, whereas conscious surrender allowed the vibration to stabilize into a clear resonance.
“The Gateway Process uses Hemi-Sync techniques to achieve a state of high brainwave coherence, creating altered states of consciousness where the physical body sleeps while the mind remains awake… As this coherence builds, subjects describe a vibrational threshold—an intense whole-body somatic resonance or electromagnetic buzzing—that precedes the functional phase-shifting of consciousness beyond the physical coordinate system. This represents an inductive phase shift where the biofield decouples from structural cellular constraints.” — McDonnell, C. I., Lieutenant Colonel, USA. Analysis and Assessment of Gateway Process, US Army Intelligence and Security Command (1983), declassified under CIA-RDP96-00788R001700210016-5.
Monroe discovered that by consciously modulating this internal vibration—mentally matching its frequency to an internal reference node and visualizing the oscillation sweeping like a longitudinal standing wave across his limbs—he could break the physical-somatic bond at will. This realization led to the development of the Monroe Institute’s Gateway Experience protocol, detailed further in our analysis of the Monroe Gateway Experience protocol.
3.2 Esoteric Lineages: Kundalini Vayu Resonances and Tantric Pranamaya Tremors
Monroe’s discovery of the vibrational stage was not unprecedented; it reflects experiential milestones well documented within Eastern contemplative traditions. Within the Shakta and Shaiva Tantric lineages, the transition across somatic boundaries is known as prana-uthana, or the upward surging of the subtle vital force. Classical treatises such as the Vigyan Bhairav Tantra and the Shat-Chakra-Nirupana contain precise phenomenological descriptions of intense whole-body vibrations, termed spanda (dynamic divine vibration) or kampa (somatic trembling).
In these lineages, the physical frame is animated by the pranamaya kosha, the subtle energetic sheath. Under ordinary conditions, the primary pranic currents (Ida and Pingala) cycle rhythmically, maintaining physiological homeostasis and structural cellular binding. However, when sensory input is systematically withdrawn via pratyahara, the dual currents collapse into the central neural axis (Sushumna Nadi). This unifies autonomic activity, eliciting the classical tremors of early kundalini awakening.
+-------------------------------------------------------------------------+
|                  ESOTERIC TO NEUROBIOLOGICAL CONVERGENCE                |
+--------------------------+----------------------------------------------+
| Tantric / Yogic Concept  | Neurobiological & Psychoacoustic Correlate   |
+--------------------------+----------------------------------------------+
| Prana-Uthana             | Pontine-Spinal Glycinergic Motor Inhibition  |
| Spanda / Kampa (Tremors) | Micro-Gamma Synchrony across Sensorimotor    |
|                          | Strips on slow Theta/Delta Baselines         |
| Ida / Pingala Balance    | Hemispheric-Synchronization (Bilateral FFR)  |
| Sushumna Entry           | TPJ Attenuation & Egocentric Decoupling      |
+--------------------------+----------------------------------------------+
These structural parallels demonstrate that Monroe’s observations mirror ancient contemplative maps. Whether interpreted as the purification of cellular nadis or as the disruption of thalamocortical sensory integration, the phenomenon marks the same physiological event: the motor-sensory apparatus decoupling from the central seat of executive awareness, detailed extensively in our exploration of kundalini awakening neurobiology.
3.3 Micro-Coherence and the Toroidal Biofield Dynamic
Moving beyond localized neuroanatomy, the vibrational stage also points to macro-level biophysical changes across the human organism. The human body functions as a complex, continuous emitter of low-frequency electromagnetic fields, generated by the rhythmic contractions of the myocardium, the saltatory conduction of peripheral nerve bundles, and the oscillatory dipole activity of cerebral neural columns.
Under ordinary waking conditions, these electromagnetic fields are phase-scattered and noisy, characterized by wide spectral variance and low spatial coherence. During deep, resonant autonomic regulation, the heart’s rhythmic acoustic output entrains global circulatory systems, producing a coherent standing wave that radiates throughout the body.
This cardiovascular-cerebral phase synchronization organizes the body’s subtle biofield into a coherent, self-sustaining toroidal geometry. The somatic tremors represent an inductive phase transition. Just as an alternating current passing through an inductor generates a magnetic flux that can decouple from its source conductor, the human bioelectric matrix achieves a state of micro-coherence where internal electromagnetic patterns no longer bind to the dense physical cellular scaffold. A comprehensive physical analysis of these parameters is available in our study of biofield electrodynamics and consciousness.
4. Step-by-Step Experiential Protocol: Inducing and Navigating the Vibrational State
4.1 Phase I: Sensorimotor Deprivation and Hemispheric Entrainment Setup
Systematic induction of the vibrational state demands total elimination of competitive ambient sensory inputs. The nervous system cannot decouple its internal mapping networks while continuously responding to tactile, thermal, or auditory interruptions.
STAGE 1                      STAGE 2                      STAGE 3
+--------------------+        +--------------------+        +--------------------+
| SENSORY DEPTH      |        | AUTONOMIC RESET    |        | POLARITY ROTATION  |
| - Supine Alignment |  ===>  | - 4:7:8 Respiration|  ===>  | - Sweep Oscillations|
| - 196 Hz Carrier   |        | - Parasympathetic  |        | - Phase Boundary   |
| - 4.5 Hz Theta Beat|        |   Dominance        |        |   Ejection         |
+--------------------+ +--------------------+ +--------------------+- Environmental Preparation: Position the physical body in absolute supine alignment, minimizing neck flexion and eliminating all physical points of pressure. Ambient room temperature must be regulated to precisely 21–23°C to prevent shivering or peripheral vasoconstriction. Total darkness must be maintained via a light-occluding sleep mask.
- Audio Delivery Architecture: Utilize calibrated over-ear headphones capable of accurate low-frequency reproduction down to 20 Hz. Deliver a continuous 196 Hz carrier tone paired with an asymmetric right-channel 200.5 Hz frequency, producing a targeted 4.5 Hz Theta binaural beat. Pink noise must be mixed into the acoustic baseline at a ratio of -18 dB to mask external transient acoustics and soften auditory cortex vigilance.
- Somatic Relaxation Vector: Systematically traverse the physical body with passive interoception, starting from the distal toes and ascending toward the cranio-facial muscles. Actively release residual muscular tension within the masseter, ocular, and tongue complexes, as motor firing in these areas blocks descending glycinergic spinal inhibition.
4.2 Phase II: Resonant Box-Breathing and Autonomic Down-Regulation
Once external inputs are suppressed, the practitioner must systematically lower autonomic arousal. The heart-rate variability (HRV) profile must transition from sympathetic dominance to high-amplitude vagal tone to support central motor atonia.
- Respiration Architecture: Initiate a precise 4:7:8 breathing rhythm. Inhale diaphragmatically through the nasal passages for 4 continuous seconds; hold the breath without tightening the glottis for 7 seconds; exhale smoothly through relaxed lips for 8 seconds.
- Physiological Effects: The extended exhalation stimulates the pulmonary branches of the vagus nerve, releasing acetylcholine directly into the sinoatrial node. This lowers systemic cardiac output and initiates down-regulation of the ascending locus coeruleus-noradrenaline system.
- Cognitive Disengagement: Disengage conscious manipulation of internal cognitive narratives. Assume the stance of a detached, passive observer, monitoring internal physiological sensations without assigning narrative significance. Allow hypnagogic phenomena to pass without analytical focus, maintaining vigilance on the central acoustic beat.
4.3 Phase III: Phase-Modulating the Somatic Oscillations to Facilitate Exit
As the physical body crosses into sleep paralysis, the vibrational stage will manifest suddenly, presenting as an intense internal surge, an electrical hum, or mechanical trembling throughout the frame. Navigating this threshold requires absolute passive stability:
Target Brainwave Frequency: 4.5 Hz (Theta) | Carrier Wave: 196 Hz (G3) paired dichotically with 200.5 Hz. Breathing Cadence: 4-second inhalation, 7-second intra-thoracic retention, 8-second slow linear exhalation. Motor Execution Directives: Zero somatic resistance. Maintain passive, non-reactive awareness as the tremors emerge.
Step-by-Step Decoupling Instructions:
- Neutral Observation: When somatic tremors start, make no physical effort to move, calibrate, or fight the vibration. Any active motor recruitment instantly activates motor cortex pathways, terminating sleep paralysis.
- Oscillation Sweeping: Direct internal attention toward the base of the skull (occiput). Visualize and feel the vibration collecting into a dense energetic node at this point. Mentally sweep this focal node down the spine toward the feet, and then draw it back to the crown in a smooth, rhythmic cycle matching your 4.5 Hz entrainment rate.
- Phase-Boundary Push: Once the entire body resonates in an uninterrupted longitudinal standing wave, visualize a secondary point of awareness 30 centimeters directly above your physical forehead. Shift your spatial frame of reference to this elevated coordinate. Execute an internal roll, floating ascent, or clean upward release to decouple from the physical substrate.
5. Differentiation: Vibrational Threshold vs. Neurological Pathologies
5.1 Hypnagogic Sleep Paralysis vs. Controlled Vibrational Decoupling
Because the vibrational state shares its fundamental motor-inhibition pathway with classical sleep paralysis, distinguishing the two relies on phenomenological presentation, psychological orientation, and underlying autonomic dynamics. In uncontrolled sleep paralysis, the subject awakens unexpectedly into an uncoordinated REM-intrusion state. Executive control within the dorsolateral prefrontal cortex remains impaired, and the amygdala responds with intense terror, often projecting menacing hypnagogic imagery (such as the classical “incubus” or shadow figure) into the perceptual field.
Conversely, protocol-induced vibrational states involve maintained executive clarity. The practitioner enters the threshold voluntarily, keeping prefrontal monitoring intact. Rather than experiencing the sensation of external suffocating pressure or terror, the subject recognizes the somatic tremor as an endogenous energetic uncoupling. While involuntary sleep paralysis features severe sympathetic hyper-arousal (tachycardia, shallow respiration, and panic), controlled vibrational decoupling maintains parasympathetic stability, transforming what is typically a terrifying medical intrusion into an intentional, reproducible gateway for extra-somatic departure.
5.2 Focal Motor Seizures and Paroxysmal Sensory Phenomena
A critical diagnostic distinction must be drawn between the vibrational state and focal motor seizures originating in the frontal or temporal lobes. Paroxysmal neurological episodes can produce somatic tingling, motor jerks, and altered bodily perceptions that may superficially mimic pre-separation tremors.
Controlled Vibrational State
- Onset Mechanism: Voluntary protocol engagement via sensory deprivation and psychoacoustic entrainment.
- EEG Markers: Stable 4.0–6.0 Hz Theta baseline overlaid with transient 40–80 Hz cortical micro-gamma bursts.
- Subject Agency: Intact executive lucidity; able to passively sustain, modulate, or terminate the state.
- Post-Event State: Complete cognitive clarity, absence of physical confusion, and enhanced emotional vitality.
- Physical Risk: Zero neuromuscular trauma; standard physiological sleep-paralysis mechanics.
Clinical Sleep Paralysis
- Onset Mechanism: Involuntary, disruptive awakening during non-synchronized REM motor-atonia transitions.
- EEG Markers: Mixed-frequency REM patterns; dysregulated Alpha-Theta coherence; hyperactive amygdala activation.
- Subject Agency: Severe panic, perceived external oppression, and temporary inability to regain motor control.
- Post-Event State: Residual sympathetic exhaustion, acute anxiety, and fragmented cognitive alertness.
- Physical Risk: Psychological distress; secondary sleep fragmentation and elevated chronic fatigue.
Temporal Lobe Seizure
- Onset Mechanism: Involuntary, uncontrolled paroxysmal electrical discharges within limbic or temporal cortical regions.
- EEG Markers: High-amplitude, pathological sharp-wave epileptiform spike-and-wave discharges.
- Subject Agency: Severely compromised; clouding or loss of consciousness; involuntary motor automatisms.
- Post-Event State: Prolonged post-ictal state with confusion, memory loss, headaches, and focal motor weakness.
- Physical Risk: Neurotoxicity from continuous seizure activity; danger of falls or physical self-injury.
5.3 Panic-Induced Paresthesia and Hyperventilation Artifacts
A final clinical differential involves somatic paresthesias caused by hyperventilation and respiratory alkalosis. Inexperienced practitioners who attempt vibrational induction without disciplined breathing often adopt an unconscious, rapid thoracic breathing pattern. This excessive ventilation blows off carbon dioxide ($CO_2$), inducing hypocapnia and raising systemic blood pH.
This resulting alkalosis decreases serum levels of ionized calcium, increasing peripheral nerve excitability. The subject experiences lightheadedness, perioral tingling, and carpopedal spasms—somatic prickling in the hands, face, and feet that can be easily mistaken for the early vibrational state. However, hyperventilation paresthesia is physically distinct from genuine vibrational decoupling: it is accompanied by muscular tetany and peripheral constriction, whereas the genuine vibrational threshold is characterized by profound neuromuscular flaccidity, motor atonia, and an internal, whole-body electrical hum that does not rely on systemic hypocapnia.
6. Operational Safety, Contraindications & Biofield Grounding
6.1 Photosensitive and Psychoacoustic Epileptogenic Risks
The systematic use of acoustic entrainment to trigger the vibrational state introduces specific physiological stressors that must be carefully managed. Introducing low-frequency binaural difference tones within the Theta and Alpha spectra directly influences thalamocortical pacemakers. For the vast majority of healthy adults, this process is physiologically benign; however, individuals with a personal or familial history of seizure disorders, cortical dysrhythmias, or diagnosed idiopathic epilepsy face meaningful clinical risks.
While auditory beats alone are less epileptogenic than stroboscopic photic stimulation, their combination—often found in multimodal mind machines—can lower the seizure threshold. Entraining neural columns toward synchronized 4–7 Hz Theta bands can trigger subclinical paroxysmal activity in structurally vulnerable brains, potentially turning a meditative attempt into an uncontrolled focal seizure. Practitioners with diagnosed neurological conditions must strictly avoid rapid psychoacoustic driving protocols.
Strict Clinical Contraindications:
- Diagnosed epilepsy, structural cortical lesions, or a history of unprovoked seizures.
- Active cardiovascular instability, including sustained cardiac arrhythmias, uncontrolled hypertension, or severe coronary artery disease. The sudden onset of tremors can trigger acute autonomic stress responses.
- Active psychiatric conditions characterized by fragile ego integrity, specifically Dissociative Identity Disorder, severe Depersonalization/Derealization Disorder (DPDR), or acute Borderline Personality Organization.
- Implantation of electronic medical hardware, including cardiac pacemakers, deep-brain stimulation units, or cochlear implants, which may interact unpredictably with neuro-acoustic driving setups.
Mandatory Immediate Termination Protocol: If severe focal motor twitching, sharp cranial pain, or profound cardiac distress occurs during induction, abort the protocol immediately: break the respiratory rhythm with forceful exhalations, vigorously wiggle the distal extremities (toes and fingers), open the eyes fully to baseline illumination, and engage in firm physical tactile anchoring.
6.2 Dissociative Depersonalization Vulnerabilities in Fragile Ego Structures
The psychological risks associated with out-of-body decoupling center primarily around dissociative tendencies. Deliberately suppressing the right temporoparietal junction and disrupting vestibular-somatosensory integration weakens ordinary egocentric boundaries. For a practitioner with a resilient, well-integrated ego, this dissolution is experienced as an expansive, liberating milestone of consciousness.
However, for individuals with baseline depersonalization/derealization disorder (DPDR) or borderline psychological organization, this uncoupling can precipitate acute fragmentation. If a subject already relies on fragile defensive structures to separate inner psychological contents from external reality, inducing a literal out-of-body state can shatter their sense of grounded presence. The resulting post-session state may involve persistent dissociative fugue, profound derealization, panic-inducing alienation from the physical reflection, and acute existential dread. Controlled extraction protocols require robust psychological resilience and clear emotional self-regulation.
6.3 Somatic Re-Entry and Biofield Grounding Mechanics
The process of terminating a projection session and returning to the physical vessel demands just as much methodical precision as the initial vibrational exit. Rushing somatic re-entry or experiencing a sudden, startled awakening from the vibrational threshold can leave the practitioner with lingering post-projection malaise—a state marked by spatial disorientation, lingering vestibular vertigo, dull cranial pressure, and mild motor ataxia.
STEP 1                      STEP 2                      STEP 3
+--------------------+        +--------------------+        +--------------------+
| DISTAL ACTIVATION  |        | KINETIC INTEGRATION|        | METABOLIC GROUNDING|
| - Micro-twitches   |  ===>  | - Axial rotation   |  ===>  | - Thermal reset    |
| - Interoceptive    |        | - Dynamic tactile  |        | - Hydration & Salt |
|   reconnection     |        |   engagement       |        |   replenishment    |
+--------------------+ +--------------------+ +--------------------+- Distal Motor Activation: To initiate reintegration, focus attention entirely on the most distal motor effectors: the toes and fingertips. Attempt minute, micro-millimeter contractions. This sends ascending afferent volleys up peripheral nerves, signaling descending pontine tracts to turn off glycinergic motor inhibition.
- Kinetic Re-Integration: Once peripheral movement returns, engage the masseter muscles by swallowing, then slowly open and close the eyes to recalibrate vestibular-ocular reflexes. Slowly roll the head from side to side to clear lingering spatial jitter at the rTPJ.
- Metabolic and Biofield Grounding: Sit upright smoothly and plant both bare feet firmly on the ground. Consume 250–500 mL of clean mineralized water containing a pinch of unrefined sea salt to restore electrolyte balance and support neurovascular volume. Engage in firm tactile contact with textured surfaces, anchoring your full awareness back inside physical anatomy before returning to normal daily tasks.
7. Phenomenological Correlates & Veridical Evidence from Laboratory Trials
7.1 The Tart Laboratory Experiments: Veridical Identification Under EEG Control
The empirical investigation of consciousness operating beyond physical somatic confines reached a key historical milestone in the late 1960s through the rigorous laboratory work of psychologist Charles T. Tart at the University of California, Davis. Tart set out to determine whether the vibrational stage and subsequent out-of-body states represented purely internal hypnagogic hallucinations or genuine, non-local perceptual phenomena.
“In a psychophysiological study of an out-of-the-body experience in a selected female subject (Miss Z), the subject spent four non-consecutive nights sleeping in an electroencephalographic laboratory while physiological activity was continuously monitored… The subject successfully decoupled from her physical body and accurately read a random five-digit target number (43152) positioned on an elevated shelf accessible only from a vantage point near the ceiling. The electroencephalographic pattern during this verified target identification was characterized by an unusual, poorly-developed Stage 1 sleep-like pattern with prominent Alpha activity, completely devoid of rapid eye movements (REM) or motor artifacts.” — Tart, C. T. (1968). A psychophysiological study of out-of-the-body experiences in a selected subject. Journal of the American Society for Psychical Research, 62(1), 3–27.
Tart’s laboratory findings provided crucial empirical data: the physiological state underlying veridical extra-somatic projection is distinctly different from both standard dreaming REM sleep and ordinary waking consciousness. The presence of persistent, high-voltage Alpha-Theta rhythms alongside complete somatic motor quiescence and absent eye movements confirmed that Miss Z was not sleepwalking, nor was she guessing. The transition out of the physical frame, preceded by the characteristic somatic hum, enabled accurate non-local visual perception of a five-digit number whose probability of being guessed by chance was 1 in 100,000.
7.2 Monroe Institute Gateway Declassified Findings: Coherence Vectors
During the late 1970s and early 1980s, the Monroe Institute’s Gateway Experience attracted formal scrutiny from the United States military and intelligence communities. Operating under contracts via the Defense Intelligence Agency (DIA) and the US Army Intelligence and Security Command (INSCOM), analysts led by Lieutenant Colonel Wayne M. McDonnell assessed the Monroe methods for remote intelligence collection.
                    HEMISPHERIC SYNCHRONIZATION SPECTRUM
Left Hemisphere (Analytical)               Right Hemisphere (Holistic)
[ Wave Pattern A: Variable Beta ]          [ Wave Pattern B: Variable Beta ]
                     \                         /
                      \  BINAURAL INTERVENTION /
                       ========================
                       [ PHASE-LOCKED COHERENCE ]
                       [   Unified 5.5 Hz Theta ]
                                   │
                                   ▼
         [ Systemic Cardiorespiratory Standing Wave Generated ]
                                   │
                                   ▼
         [ Electrostatic Charge Decoupling from Cellular Matrix ]
The declassified 1983 document Analysis and Assessment of Gateway Process confirmed several core mechanics. McDonnell reported that Monroe’s acoustic protocols did not merely alter moods; they induced hemispheric-synchronization, wherein the electrical wave patterns of both cerebral hemispheres mirror one another in amplitude and phase. The military report documented that this synchronized brain state, combined with the body’s natural micro-vibrations from heartbeats, transforms the physical organism into a unified bioelectric oscillator. McDonnell confirmed that the vibrational stage represents the threshold where this electrostatic field achieves sufficient internal coherence to phase-shift beyond physical spatial limits.
7.3 Neurochemical Bridges: Endogenous Tryptamines and the Threshold Surge
The intense, buzzing sensory phenomena that characterize the vibrational threshold have led neurochemists to explore potential endogenous biochemical triggers. Emerging models focus on the interplay between standard sleep neurochemistry and the trace amine and endogenous tryptamine pathways within the mammalian brain, notably N,N-dimethyltryptamine (endogenous DMT) and its precursor, tryptamine.
Modern analytical methodologies have confirmed the expression of indolethylamine N-methyltransferase (INMT)—the critical enzyme required for DMT synthesis—within the mammalian pineal gland, cerebral cortex, and spinal cord. Under baseline conditions, INMT expression is metabolically restrained. However, during acute neurophysiological transitions, such as the onset of rapid-eye-movement motor atonia or near-death hypoxia, localized surges of trace amines may be released directly into the central nervous system.
When endogenous tryptamines bind to 5-$HT_{2A}$ and trace amine-associated receptors (TAAR) across the sensorimotor cortex, they rapidly reorganize thalamocortical sensory routing. This biochemical cascade, paired with simultaneous pontine motor inhibition, produces the subjective sensation of an internal high-voltage electrical hum and sets up the structural dissociation that enables astral projection.
8. Frequently Asked Questions Regarding the Vibrational State
8.1 How can a practitioner overcome the intense fear response when somatic tremors begin?
The sudden emergence of somatic tremors often triggers a primal, instinctual panic response. This reaction is entirely neurobiological: because descending pontine circuits have locked somatic motor neurons via glycinergic inhibition, the brain suddenly perceives itself as paralyzed and helpless. The amygdala registers this rapid loss of motor agency as an existential threat, prompting an immediate surge of adrenaline that spikes heart rates and shatters the delicate sleep paralysis equilibrium.
Overcoming this autonomic survival reflex requires cognitive restructuring and progressive desensitization. The practitioner must anticipate this threshold as a natural physiological marker of success rather than a medical emergency. When the buzzing begins, resist the impulse to verify physical motor control; testing muscle movement immediately wakes the motor cortex and terminates the state. Instead, focus entirely on the respiration cycle, surrender all physical resistance, and passively lean into the vibration, treating the tremor as an acoustic or energetic wave passing naturally through the physical frame.
8.2 What should be done if the vibrations stall or fail to culminate in separation?
In many induction attempts, the somatic tremors manifest with intense clarity but stall out, failing to trigger an out-of-body departure before eventually fading away. This stagnation typically traces back to localized muscular bracing—often subtle clenching of the jaw, tension around the eyes, or shallow, irregular breathing patterns that anchor awareness back inside the somatic frame.
REMEDY FOR STALLED SOMATIC OSCILLATIONS
+-------------------------------------------------------------------+
| 1. STALL RECOGNITION: Tremors stabilize without physical exit.    |
| 2. SOMATIC SCAN: Detect subtle tension in eyes, throat, or jaw.   |
| 3. ATTENTION SWEEP: Trace the vibration longitudinally (Crown-Toe)|
| 4. AMPLITUDE ACCELERATION: Intensify frequency via breath hold.   |
| 5. PHASE DISPLACEMENT: Execute vertical extraction visualization. |
+-------------------------------------------------------------------+
To clear this energetic plateau, take conscious control of the vibration through focused interoception. Sweep the felt sense of the vibration upward from your toes to the crown of your head, transforming the static tremor into an active, longitudinal standing wave. Match this sweeping motion to the subtle rhythm of your breathing. Once the whole body hums as a coherent unit, apply an extraction visualization: imagine climbing a physical rope above you, feeling a powerful upward gravitational pull, or mentally rotating your body 180 degrees along its central axis. Shifting your spatial awareness cleanly detaches consciousness from the immobilized physical frame.
8.3 Can physical injury or cardiac arrest occur during high-intensity energetic buzzing?
Despite the visceral intensity of the vibrational state—which subjects frequently describe as feeling like an electric shock or powerful mechanical shaking—the phenomenon carries no risk of physical injury or cardiac failure for an individual with a healthy cardiovascular system. Physiological monitoring during lab experiments shows that this “buzzing” does not involve actual mechanical muscle tearing or erratic, dangerous cardiac rhythms.
The sensation of high-frequency vibration is entirely neuro-perceptual, generated by the sudden uncoupling of somatosensory mapping in the right temporoparietal junction alongside cortical micro-gamma bursts. While a momentary panic reaction may cause transient sinus tachycardia, the cardiovascular system is under no more strain than it would experience during a vivid dream. Provided the practitioner does not suffer from serious underlying cardiovascular conditions or unmanaged epilepsy, the vibrational threshold remains an entirely safe, reproducible, and transformative gateway into extra-somatic consciousness. :::